
What Is the Newest Type of Knee Surgery?
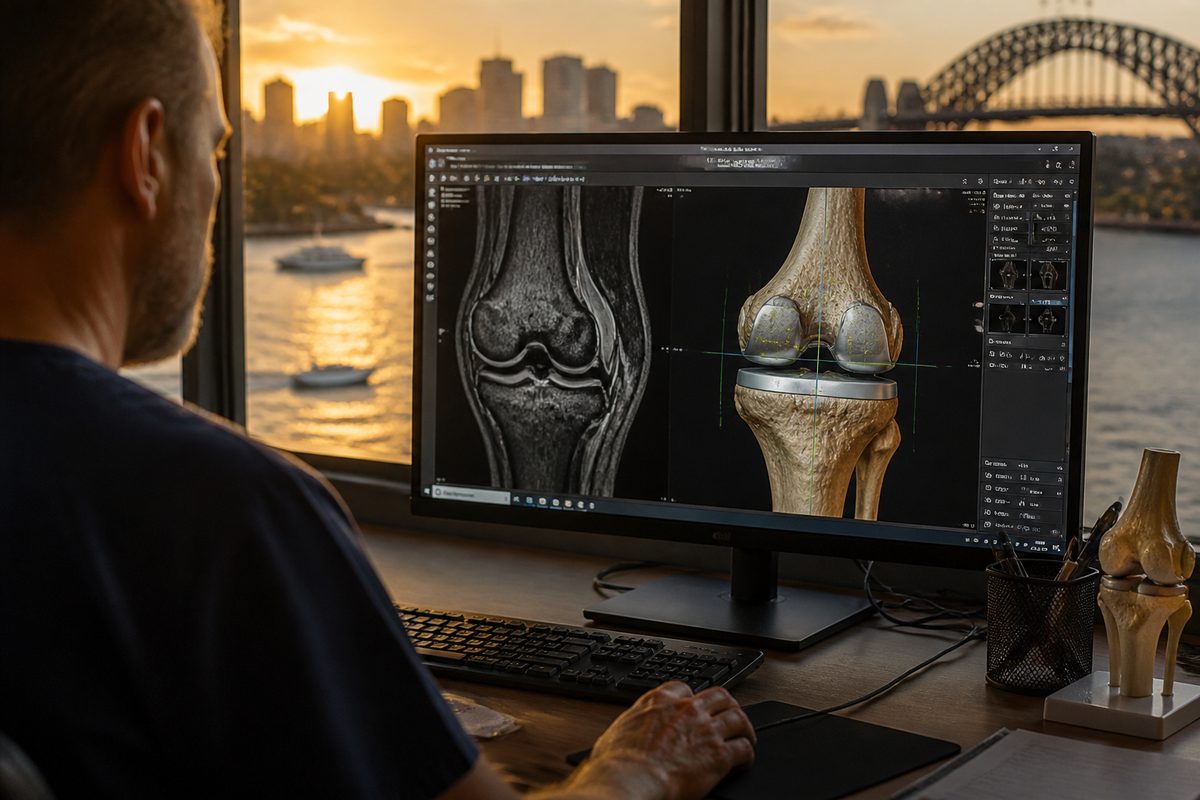
Robotic-assisted knee replacement is the newest widely discussed knee operation, but it has not been proven better than conventional knee replacement. Surgeons are adopting it hoping to help the patients who stay unhappy after an otherwise successful operation. The big trials that will test that hope are still under way. That is my reading of the evidence, not a study result: newer does not automatically mean better.
So the useful question is not which surgery is newest. It is which option fits your knee, and what a new tool really adds for you.
What makes robotic knee replacement new?
The operation itself is the same idea as before. The surgeon removes worn joint surfaces and fits a metal and plastic implant. What changes is how the cuts are planned and guided. A robotic arm helps the surgeon place the implant to a pre-set plan. The surgeon still runs the operation.
Many systems start with a CT scan of your knee. The scan builds a 3D model, and the surgeon plans the implant position on it before surgery. In theory, tighter placement should mean a joint that feels more natural.
That is the theory. Theory and results are different things.
Does the robot give better results?
Nobody can say yet. A major multicentre randomised trial programme is comparing robotic and conventional knee replacement in people with knee osteoarthritis. It measures how aware patients are of their new joint after a year, and it also looks at cost-effectiveness.
That measure matters. A good knee replacement is one you forget about. Until those results arrive, a claim of clear advantage is a sales pitch, not a fact.
Think of a patient who sees a clinic ad with the word "robotic" in big letters. She assumes it means safer and faster. It might mean neither. What it means for sure is a different tool in the room, and possibly a different bill.
Which questions should you ask a surgeon who offers it?
Ask these before you agree:
- What does the robotic approach add for my knee, compared with the standard method?
- How many of these operations have you done?
- Does it change my cost, or my recovery plan?
A confident surgeon answers plainly. A vague answer tells you something too.
Surgeon skill matters as much as the technology. A very experienced surgeon using a conventional method can beat a beginner with the shiniest machine. Your own knee problem matters just as much, because the best operation depends on what is actually wrong.
What other new knee treatments exist?
Robotic knee replacement gets the headlines, yet it is only one of several newer ideas. Most of the others target earlier stages of knee trouble, when a full replacement is too much.
Genicular artery embolization
Genicular artery embolization is a procedure done through a small puncture, usually in the groin or wrist. A doctor guides a catheter to the small arteries around the knee and blocks some of them. The goal is to reduce the inflamed lining that drives pain in an arthritic knee. It is aimed at pain relief, not at rebuilding the joint. Ask the treating team how much long-term evidence exists for your situation, because this is a young field.
Cartilage repair with your own cells
Autologous chondrocyte implantation is a cartilage repair method. Surgeons take a small sample of your own cartilage cells, grow them in a lab, and place them in a cartilage hole in the knee. It is meant for focal damage in a younger knee, not a joint worn out across the board. It takes two procedures and a long rehab.
Biologic injections
Platelet-rich plasma is made from your own blood. It is spun to concentrate platelets and then injected into the knee. Stem-cell therapy goes a step further and uses cells, often a mesenchymal stem cell product, in the hope of calming inflammation or aiding repair. Both are heavily advertised. Results vary, products are not standardised, and clinics differ widely in what they inject. Be wary of any provider who promises that your cartilage will grow back.
Is newer surgery right for ligament and meniscus injuries?
Not every knee problem is arthritis. Sports injuries need their own thinking.
A meniscus tear may be repaired, trimmed or simply treated without surgery, depending on the tear type and your symptoms. Many people do well with a structured rehab programme first.
Anterior cruciate ligament reconstruction replaces a torn ligament with a graft. Surgeons choose from several graft sources. One option is the quadriceps tendon, taken from the front of the thigh. It has gained attention in recent years. It is a choice among reasonable options, not a magic upgrade, so ask your surgeon why they favour one graft over another for you.
Here is the pattern. In each case, the "new" choice solves a specific problem for a specific kind of knee. It does not replace the older choice for everyone.
Why does newer not mean better?
Medicine has a habit of judging a technique by how modern it feels. The better test is whether it helps people more than the old way, over years.
Consider a dental implant. It works well because it is a mature technology that has been refined and followed up for a long time. Organ transplantation is another example. It became routine only after decades of work on surgical methods and long-term follow-up. Good techniques earn trust slowly. A treatment that is two years old has not had that time.
That does not make new options bad. Robotic assistance may well turn out to help. The point is simple. You should be told the truth about what is known and what is a hope.
Do you need surgery at all?
Many people reach for surgery before they have tried the basics. Physical therapy is a first-line treatment for a lot of knee pain. Strengthening the muscles around the knee takes load off the joint. It costs less than surgery and carries far less risk.
Other non-surgical steps can sit alongside it. Weight loss, activity changes, and pain-relieving injections all have a place. Pain control is also getting better around surgery. A nerve block, for example, numbs the area around the knee so early recovery hurts less and you can start moving sooner.
Picture a man in his sixties with a stiff, aching knee who is certain he needs the newest operation. His scan shows moderate wear. After a few months of rehab and weight loss, his pain falls enough that he postpones surgery. That outcome is common enough to be worth considering before you book anything. If his pain had not eased, he would at least have walked into the surgeon's office knowing what he had already tried.
How do you compare your options sensibly?
Start with the problem, not the product. Ask what exactly is wrong with your knee. Is it cartilage damage in one spot, a torn ligament, or wear across the whole joint? The answer narrows your options fast.
Then ask for the range. A good surgeon will describe the standard option, any newer option, and doing nothing yet. If you only hear one choice, get a second opinion. It is a normal request and good surgeons expect it.
Finally, ask about proof. What are the results for patients like you? Is the treatment backed by completed trials, or is it still being tested? Honest surgeons will tell you which is which.
Cost belongs in this conversation too. If a robotic approach adds a charge, ask what you receive for it. The trials mentioned earlier include cost-effectiveness for exactly this reason.
What should you do next?
- Get a clear diagnosis of your knee problem, including imaging, before you compare any operations.
- Try or finish a physical therapy programme if you have not already.
- If a surgeon suggests robotic knee replacement, ask what it adds for your knee, how many they have done, and what it costs.
- For any injection or procedure marketed as new, ask what the trial evidence shows for your exact condition.
- Book a second opinion before you commit to surgery.
The best knee operation is the one that fits your problem and is done by someone who does it often. Newness is a sales feature. Fit and skill are what you should shop for.
Sources
- Aggarwal V, Sun J, Sambandam S (2024) "Outcomes following robotic assisted total knee arthroplasty compared to conventional total knee arthroplasty" Archives of Orthopaedic and Trauma Surgery. DOI: 10.1007/s00402-024-05231-7
- Khatri C, Metcalfe A, Wall P, Underwood M, Haddad FS, Davis ET (2024) "Robotic trials in arthroplasty surgery" The bone & joint journal. PMID: 38295854